bookmark_borderCollapse Of West Antarctica

The collapse of the ice sheet in West Antarctica have raised concern about the rising sea level.

“This is really happening,” Thomas P. Wagner, who runs NASA’s programs on polar ice, said. “There’s nothing to stop it now. But you are still limited by the physics of how fast the ice can flow.”

“Today we present observational evidence that a large sector of the West Antarctic ice sheet has gone into irreversible retreat,” Dr. Rignot said in the NASA news conference. “It has passed the point of no return.”

“Even if the warm water now eating away at the ice were to dissipate, it would be too little, too late to stabilize the ice sheet,” Dr. Joughin said. “There’s no stabilization mechanism.”

“If we have indeed lit the fuse on West Antarctica, it’s very hard to imagine putting the fuse out,” Dr. Alley said. “But there’s a bunch more fuses, and there’s a bunch more matches, and we have a decision now: Do we light those?”

The NASA study says:
A new study by researchers at NASA and the University of California, Irvine, finds a rapidly melting section of the West Antarctic Ice Sheet appears to be in an irreversible state of decline, with nothing to stop the glaciers in this area from melting into the sea.

The study presents multiple lines of evidence, incorporating 40 years of observations that indicate the glaciers in the Amundsen Sea sector of West Antarctica “have passed the point of no return,” according to glaciologist and lead author Eric Rignot, of UC Irvine and NASA’s Jet Propulsion Laboratory (JPL) in Pasadena, California. The new study has been accepted for publication in the journal Geophysical Research Letters.

These glaciers already contribute significantly to sea level rise, releasing almost as much ice into the ocean annually as the entire Greenland Ice Sheet. They contain enough ice to raise global sea level by 4 feet (1.2 meters) and are melting faster than most scientists had expected. Rignot said these findings will require an upward revision to current predictions of sea level rise.

“This sector will be a major contributor to sea level rise in the decades and centuries to come,” Rignot said. “A conservative estimate is it could take several centuries for all of the ice to flow into the sea.”

Three major lines of evidence point to the glaciers’ eventual demise: the changes in their flow speeds, how much of each glacier floats on seawater, and the slope of the terrain they are flowing over and its depth below sea level. In a paper in April, Rignot’s research group discussed the steadily increasing flow speeds of these glaciers over the past 40 years. This new study examines the other two lines of evidence.

The glaciers flow out from land to the ocean, with their leading edges afloat on the seawater. The point on a glacier where it first loses contact with land is called the grounding line. Nearly all glacier melt occurs on the underside of the glacier beyond the grounding line, on the section floating on seawater.

Just as a grounded boat can float again on shallow water if it is made lighter, a glacier can float over an area where it used to be grounded if it becomes lighter, which it does by melting or by the thinning effects of the glacier stretching out. The Antarctic glaciers studied by Rignot’s group have thinned so much they are now floating above places where they used to sit solidly on land, which means their grounding lines are retreating inland.

“The grounding line is buried under a thousand or more meters of ice, so it is incredibly challenging for a human observer on the ice sheet surface to figure out exactly where the transition is,” Rignot said. “This analysis is best done using satellite techniques.”

The team used radar observations captured between 1992 and 2011 by the European Earth Remote Sensing (ERS-1 and -2) satellites to map the grounding lines’ retreat inland. The satellites use a technique called radar interferometry, which enables scientists to measure very precisely — within less than a quarter of an inch — how much Earth’s surface is moving. Glaciers move horizontally as they flow downstream, but their floating portions also rise and fall vertically with changes in the tides. Rignot and his team mapped how far inland these vertical motions extend to locate the grounding lines.

The accelerating flow speeds and retreating grounding lines reinforce each other. As glaciers flow faster, they stretch out and thin, which reduces their weight and lifts them farther off the bedrock. As the grounding line retreats and more of the glacier becomes waterborne, there’s less resistance underneath, so the flow accelerates.

Slowing or stopping these changes requires pinning points — bumps or hills rising from the glacier bed that snag the ice from underneath. To locate these points, researchers produced a more accurate map of bed elevation that combines ice velocity data from ERS-1 and -2 and ice thickness data from NASA’s Operation IceBridge mission and other airborne campaigns. The results confirm no pinning points are present upstream of the present grounding lines in five of the six glaciers. Only Haynes Glacier has major bedrock obstructions upstream, but it drains a small sector and is retreating as rapidly as the other glaciers.

The bedrock topography is another key to the fate of the ice in this basin. All the glacier beds slope deeper below sea level as they extend farther inland. As the glaciers retreat, they cannot escape the reach of the ocean, and the warm water will keep melting them even more rapidly.

The accelerating flow rates, lack of pinning points and sloping bedrock all point to one conclusion, Rignot said.

“The collapse of this sector of West Antarctica appears to be unstoppable,” he said. “The fact that the retreat is happening simultaneously over a large sector suggests it was triggered by a common cause, such as an increase in the amount of ocean heat beneath the floating sections of the glaciers. At this point, the end of this sector appears to be inevitable.”

Because of the importance of this part of West Antarctica, NASA’s Operation IceBridge will continue to monitor its evolution closely during this year’s Antarctica deployment, which begins in October. IceBridge uses a specialized fleet of research aircraft and the most sophisticated suite of science instruments ever assembled to characterize changes in thickness of glaciers, ice sheets and sea ice.
bookmark_borderSelf-healing Materials: Vascular Blood-like Plastic

Self-healing materials have been a breakthrough in this millennium. “Self-healing materials are a class of smart materials that have the structurally incorporated ability to repair damage caused by mechanical usage over time. The inspiration comes from biological systems, which have the ability to heal after being wounded. Initiation of cracks and other types of damage on a microscopic level has been shown to change thermal, electrical, and acoustical properties, and eventually lead to whole scale failure of the material. Usually, cracks are mended by hand, which is unsatisfactory because cracks are often hard to detect. A material that can intrinsically correct damage caused by normal usage could lower costs of a number of different industrial processes through longer part lifetime, reduction of inefficiency over time caused by degradation, as well as prevent costs incurred by material failure. For a material to be strictly defined as self-healing, it is necessary that the healing process occurs without human intervention.” — Wikipedia

The BBC reports on a new self-healing plastic: “The polymer automatically patches holes 3cm wide, 100 times bigger than before.

Inspired by the human blood clotting system, it contains a network of capillaries that deliver healing chemicals to damaged areas.

The new material, created by engineers at the University of Illinois, is described in Science journal.

For decades scientists have dreamed of plastics that heal themselves like human skin.

Cracks in water pipes and car bonnets would seal up. Satellites could repair their own damage. Broken electronic chips in laptops and mobile phones would spontaneously sort out their own problems.”

bookmark_borderClimate Disruption

The United States of America released a report on global warming and has named the problem climate disruption.


The report +confirms that climate change is not a distant threat — it’s affecting us now.” Climate disruption is “expected to become increasingly disruptive across the nation throughout this century and beyond,” the National Climate Assessment concluded.

“President Obama has announced a series of executive actions to reduce carbon pollution, prepare the U.S. for the impacts of climate change, and lead international efforts to address global climate change.”

Due to climate change, the weather is getting more extreme Temperatures are rising across the U.S. Temperatures from 2001 to 2012 were warmer than any previous decade in every region of the United States. Explore this interactive map from the National Climate Assessment to learn more.

EXTREME WEATHER EVENTS
Droughts, Wildfires, and Floods are all more frequent and intense. Precipitation was 2.57 inches below the 20th Century Average. Wildfires burned more than 9.3 million U.S. acres.

Extreme weather comes at a cost

Climate and weather disasters in 2012 alone cost the American economy more than $100 billion

$30 Billion U.S. drought/heatwave

$65 Billion Superstorm Sandy

$11.1 Billion Combined severe weather

$1 Billion Western wildfires

$2.3 Billion Hurricane Isaac

There are also public health threats associated with extreme weather

Children, the elderly, and the poor are most vulnerable to a range of climate-related health effects, including those related to heat stress, air pollution, extreme weather events, and diseases carried by food, water, and insects.


We can choose to believe that Superstorm Sandy, and the most severe drought in decades, and the worst wildfires some states have ever seen were all just a freak coincidence. Or we can choose to believe in the overwhelming judgement of science — and act before it’s too late.
– President Obama

bookmark_borderRecord-Setting Rain

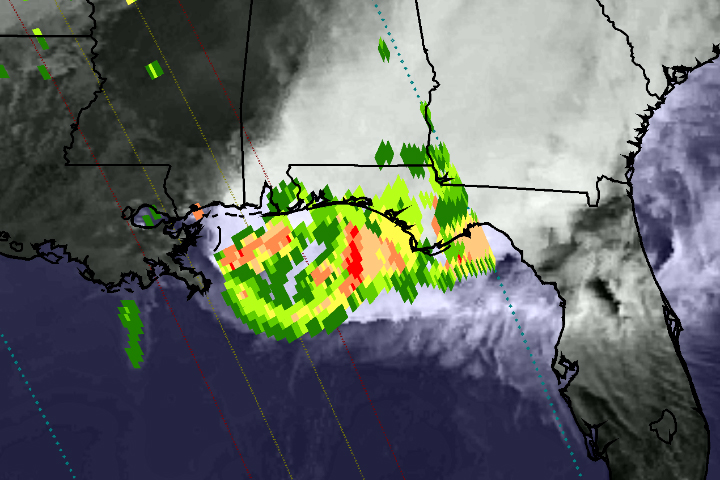
On April 29, 2014, the Global Precipitation Measurement (GPM) satellite observed the heavy rain that produced floods near Pensacola, Florida. The National Weather Service reported record-setting rainfall totals of more than 380 mm (15 inches) in Pensacola from the storm system that inundated the southeastern and eastern United States in recent days.

This image shows GPM Microwave Imager (GMI) rainfall estimates (green to red) superimposed on infrared observations (showing clouds and land) over the southeastern United States. Because the GPM satellite was launched only two months ago, the rainfall-estimation algorithms are currently undergoing a checkout period. For this reason, the scale indicates only qualitative information with green for light rain and red for heavy rain.

This GPM data was collected during a single satellite overpass shortly after noon local time, providing a snapshot of rain rates at that time. The outer blue dotted lines show the width of observations from the GMI instrument, while the two inner lines represent the area measured by the Ka-band (inner lines) and Ku-band (outer lines) of the Dual-Frequency Precipitation Radar. Once the radar data become available, they will provide a three-dimensional view of rain, ice, and snow in the atmosphere.

Extreme Weather
Extreme Weather

bookmark_borderAntimicrobial Resistance — a Serious Threat to Health

WHO’s first global report on antibiotic resistance reveals serious, worldwide threat to public health

New WHO report provides the most comprehensive picture of antibiotic resistance to date, with data from 114 countries


A new report by the World Health Organization (WHO) –its first to look at antimicrobial resistance, including antibiotic resistance, globally–reveals that this serious threat is no longer a prediction for the future, it is happening right now in every region of the world and has the potential to affect anyone, of any age, in any country. Antibiotic resistance–when bacteria change so antibiotics no longer work in people who need them to treat infections–is now a major threat to public health.

“Without urgent, coordinated action by many stakeholders, the world is headed for a post-antibiotic era, in which common infections and minor injuries which have been treatable for decades can once again kill,” says Dr Keiji Fukuda, WHO’s Assistant Director-General for Health Security. “Effective antibiotics have been one of the pillars allowing us to live longer, live healthier, and benefit from modern medicine. Unless we take significant actions to improve efforts to prevent infections and also change how we produce, prescribe and use antibiotics, the world will lose more and more of these global public health goods and the implications will be devastating.”

Key findings of the report

The report, “Antimicrobial resistance: global report on surveillance”, notes that resistance is occurring across many different infectious agents but the report focuses on antibiotic resistance in seven different bacteria responsible for common, serious diseases such as bloodstream infections (sepsis), diarrhoea, pneumonia, urinary tract infections and gonorrhoea. The results are cause for high concern, documenting resistance to antibiotics, especially “last resort” antibiotics, in all regions of the world.

Key findings from the report include:

  • Resistance to the treatment of last resort for life-threatening infections caused by a common intestinal bacteria, Klebsiella pneumoniae–carbapenem antibiotics–has spread to all regions of the world. K. pneumoniae is a major cause of hospital-acquired infections such as pneumonia, bloodstream infections, infections in newborns and intensive-care unit patients. In some countries, because of resistance, carbapenem antibiotics would not work in more than half of people treated for K. pneumoniae infections.
  • Resistance to one of the most widely used antibacterial medicines for the treatment of urinary tract infections caused by E. coli–fluoroquinolones–is very widespread. In the 1980s, when these drugs were first introduced, resistance was virtually zero. Today, there are countries in many parts of the world where this treatment is now ineffective in more than half of patients.
  • Treatment failure to the last resort of treatment for gonorrhoea–third generation cephalosporins–has been confirmed in Austria, Australia, Canada, France, Japan, Norway, Slovenia, South Africa, Sweden and the United Kingdom. More than 1 million people are infected with gonorrhoea around the world every day.
  • Antibiotic resistance causes people to be sick for longer and increases the risk of death. For example, people with MRSA (methicillin-resistant Staphylococcus aureus) are estimated to be 64% more likely to die than people with a non-resistant form of the infection. Resistance also increases the cost of health care with lengthier stays in hospital and more intensive care required.

Ways to fight antibiotic resistance

The report reveals that key tools to tackle antibiotic resistance–such as basic systems to track and monitor the problem–show gaps or do not exist in many countries. While some countries have taken important steps in addressing the problem, every country and individual needs to do more.

Other important actions include preventing infections from happening in the first place–through better hygiene, access to clean water, infection control in health-care facilities, and vaccination–to reduce the need for antibiotics. WHO is also calling attention to the need to develop new diagnostics, antibiotics and other tools to allow healthcare professionals to stay ahead of emerging resistance.

This report is kick-starting a global effort led by WHO to address drug resistance. This will involve the development of tools and standards and improved collaboration around the world to track drug resistance, measure its health and economic impacts, and design targeted solutions.

How to tackle resistance

People can help tackle resistance by:

  • using antibiotics only when prescribed by a doctor;
  • completing the full prescription, even if they feel better;
  • never sharing antibiotics with others or using leftover prescriptions.

Health workers and pharmacists can help tackle resistance by:

  • enhancing infection prevention and control;
  • only prescribing and dispensing antibiotics when they are truly needed;
  • prescribing and dispensing the right antibiotic(s) to treat the illness.

Policymakers can help tackle resistance by:

  • strengthening resistance tracking and laboratory capacity;
  • regulating and promoting appropriate use of medicines.

Policymakers and industry can help tackle resistance by:

  • fostering innovation and research and development of new tools;
  • promoting cooperation and information sharing among all stakeholders.

The report–which also includes information on resistance to medicines for treating other infections such as HIV, malaria, tuberculosis and influenza–provides the most comprehensive picture of drug resistance to date, incorporating data from 114 countries.

bookmark_borderPlanet Kepler in Habitable Zone

EARTH — NASA has discovered the first habitable planet:

Kepler Compared to Earth

Using NASA’s Kepler Space Telescope, astronomers have discovered the first Earth-size planet orbiting a star in the “habitable zone” — the range of distance from a star where liquid water might pool on the surface of an orbiting planet. The discovery of Kepler-186f confirms that planets the size of Earth exist in the habitable zone of stars other than our sun.

While planets have previously been found in the habitable zone, they are all at least 40 percent larger in size than Earth and understanding their makeup is challenging. Kepler-186f is more reminiscent of Earth.

“The discovery of Kepler-186f is a significant step toward finding worlds like our planet Earth,” said Paul Hertz, NASA’s Astrophysics Division director at the agency’s headquarters in Washington. “Future NASA missions, like the Transiting Exoplanet Survey Satellite and the James Webb Space Telescope, will discover the nearest rocky exoplanets and determine their composition and atmospheric conditions, continuing humankind’s quest to find truly Earth-like worlds.”

Although the size of Kepler-186f is known, its mass and composition are not. Previous research, however, suggests that a planet the size of Kepler-186f is likely to be rocky.

“We know of just one planet where life exists — Earth. When we search for life outside our solar system we focus on finding planets with characteristics that mimic that of Earth,” said Elisa Quintana, research scientist at the SETI Institute at NASA’s Ames Research Center in Moffett Field, Calif., and lead author of the paper published today in the journal Science. “Finding a habitable zone planet comparable to Earth in size is a major step forward.”

Kepler-186f resides in the Kepler-186 system, about 500 light-years from Earth in the constellation Cygnus. The system is also home to four companion planets, which orbit a star half the size and mass of our sun. The star is classified as an M dwarf, or red dwarf, a class of stars that makes up 70 percent of the stars in the Milky Way galaxy.

“M dwarfs are the most numerous stars,” said Quintana. “The first signs of other life in the galaxy may well come from planets orbiting an M dwarf.”

Kepler-186f orbits its star once every 130-days and receives one-third the energy from its star that Earth gets from the sun, placing it nearer the outer edge of the habitable zone. On the surface of Kepler-186f, the brightness of its star at high noon is only as bright as our sun appears to us about an hour before sunset.

“Being in the habitable zone does not mean we know this planet is habitable. The temperature on the planet is strongly dependent on what kind of atmosphere the planet has,” said Thomas Barclay, research scientist at the Bay Area Environmental Research Institute at Ames, and co-author of the paper. “Kepler-186f can be thought of as an Earth-cousin rather than an Earth-twin. It has many properties that resemble Earth.”

The four companion planets, Kepler-186b, Kepler-186c, Kepler-186d, and Kepler-186e, whiz around their sun every four, seven, 13, and 22 days, respectively, making them too hot for life as we know it. These four inner planets all measure less than 1.5 times the size of Earth.

The next steps in the search for distant life include looking for true Earth-twins — Earth-size planets orbiting within the habitable zone of a sun-like star — and measuring the their chemical compositions. The Kepler Space Telescope, which simultaneously and continuously measured the brightness of more than 150,000 stars, is NASA’s first mission capable of detecting Earth-size planets around stars like our sun.

Ames is responsible for Kepler’s ground system development, mission operations, and science data analysis. NASA’s Jet Propulsion Laboratory in Pasadena, Calif., managed Kepler mission development. Ball Aerospace & Technologies Corp. in Boulder, Colo., developed the Kepler flight system and supports mission operations with the Laboratory for Atmospheric and Space Physics at the University of Colorado in Boulder. The Space Telescope Science Institute in Baltimore archives, hosts and distributes Kepler science data. Kepler is NASA’s 10th Discovery Mission and was funded by the agency’s Science Mission Directorate.

The SETI Institute is a private, nonprofit organization dedicated to scientific research, education and public outreach. The mission of the SETI Institute is to explore, understand and explain the origin, nature and prevalence of life in the universe.

For more information about the Kepler mission, visit:

http://www.nasa.gov/kepler

bookmark_borderThe Wife Of Jesus

A fragment of papyrus known as the “Gospel of Jesus’s Wife,” caused a controversy when it was published by the Harvard Divinity School in 2012.  Now, it has been tested and the study reports “the ink and papyrus are very likely ancient, and not a modern forgery.”

The writing contains the phrases “Jesus said to them, ‘My wife…'” as well as,  “she will be able to be my disciple.”

“I took very seriously the comments of such a wide range of people that it might be a forgery,”  said Dr. King who gave the paper it’s name.  “When you have all the evidence pointing in one direction, it doesn’t make it 100 percent, but history is not a place where 100 percent is a common thing.”

Gospel of Jesus’s Wife
Gospel of Jesus’ Wife


bookmark_borderVegetarians Are Less Healthy

A new study had concluded that vegetarians are less healthy than omnivores:

Nutrition and Health – The Association between Eating Behavior and Various Health Parameters: A Matched Sample Study

Nathalie T. Burkert*, Johanna Muckenhuber, Franziska Großschadl, Eva Rasky, Wolfgang Freidl

Institute of Social Medicine and Epidemiology, Medical University Graz, Graz, Austria

Abstract

Population-based studies have consistently shown that our diet has an influence on health. Therefore, the aim of our study was to analyze differences between different dietary habit groups in terms of health-related variables. The sample used for this cross-sectional study was taken from the Austrian Health Interview Survey AT-HIS 2006/07. In a first step, subjects were matched according to their age, sex, and socioeconomic status (SES). After matching, the total number of subjects included in the analysis was 1320 (N = 330 for each form of diet – vegetarian, carnivorous diet rich in fruits and vegetables, carnivorous diet less rich in meat, and carnivorous diet rich in meat). Analyses of variance were conducted controlling for lifestyle factors in the following domains: health (self-assessed health, impairment, number of chronic conditions, vascular risk), health care (medical treatment, vaccinations, preventive check-ups), and quality of life. In addition, differences concerning the presence of 18 chronic conditions were analyzed by means of Chi-square tests. Overall, 76.4% of all subjects were female. 40.0% of the individuals were younger than 30 years, 35.4% between 30 and 49 years, and 24.0% older than 50 years. 30.3% of the subjects had a low SES, 48.8% a middle one, and 20.9% had a high SES. Our results revealed that a vegetarian diet is related to a lower BMI and less frequent alcohol consumption. Moreover, our results showed that a vegetarian diet is associated with poorer health (higher incidences of cancer, allergies, and mental health disorders), a higher need for health care, and poorer quality of life. Therefore, public health programs are needed in order to reduce the health risk due to nutritional factors.

Citation: Burkert NT, Muckenhuber J, Großschadl¨ F, Rasky´ ´
E, Freidl W (2014) Nutrition and Health – The Association between Eating Behavior and Various Health
Parameters: A Matched Sample Study. PLoS ONE 9(2): e88278. doi:10.1371/journal.pone.0088278

Editor: Olga Y. Gorlova, Geisel School of Medicine at Dartmouth College, United States of America

Received May 17, 2013; Accepted January 9, 2014; Published February 7, 2014

Copyright: 2014 Burkert et al. This is an open-access article distributed under the terms of the Creative Commons Attribution License, which permits unrestricted use, distribution, and reproduction in any medium, provided the original author and source are credited.

Funding: The authors have no support or funding to report.

Competing Interests: The authors have declared that no competing interests exist. * E-mail: nathalie.burkert@medunigraz.at

Introduction

Our diet has an impact on our well-being and on our health. Studies have shown a vegetarian diet to be associated with a lower incidence of hypertension, cholesterol problems, some chronic degenerative diseases, coronary artery disease, type II diabetes, gallstones, stroke, and certain cancers [1–7]. A vegetarian diet is characterized by a low consumption of saturated fat and cholesterol, due to a higher intake of fruits, vegetables and whole-grain products [3,4,8]. Overall, vegetarians have a lower body mass index [1,4,5,7,9–12], a higher socioeconomic status [13], and better health behavior, i.e. they are more physically active, drink less alcohol, and smoke less [9,13,14]. On the other hand, the mental health effects of a vegetarian diet or a Mediterranean diet rich in fruits, vegetables, whole-grain products and fish are divergent [9,15]. For example, Michalak et al. [16] report that a vegetarian diet is associated with an elevated prevalence of mental disorders. A poor meat intake has been shown to be associated with lower mortality rates and higher life expectancy [17], and a diet which allows small amounts of red meat, fish and dairy products seems to be associated with a reduced risk of coronary heart disease as well as type 2 diabetes [18]. Additionally, evidence concerning lower rates of cancer,

colon diseases including colon cancer, abdominal complaints, and all-cause mortality is, however, inconsistent [5–7,19–22].

Not only is the intake of certain nutrients, like red meat, associated with an increased health risk [18,23–26],high-caloric intake also plays a crucial role [23,27]. Moreover, there seems to be proof that lifestyle factors like physical activity may be more crucial in lowering disease rates than individual dietary habits [20,28–29]. While, generally speaking, diets based on plants, like vegetarian diets, seem to be associated with a certain health benefit, a lower risk to contract certain chronic diseases [30], and the ability to improve health [31–32], restrictive and monotonous vegetarian diets include the risk of nutritional deficits [2,18,19,30,33]. Baines et al. [9] report that vegetarians take more medication than non-vegetarians.

To summarize, a number of studies have shown vegetarian diets and diets with poor meat intake to be associated with lower mortality rates for certain diseases. Research about the dietary habits in Austria is, however, rather sparse and mainly focused on genetic factors [33–36]. Therefore, the aim of this study was to investigate health differences between different dietary habit groups among Austrian adults.

Methods

Study Design and Study Population

The sample for this cross-sectional study was taken from the Austrian Health Interview Survey (AT-HIS) which ran from March 2006 to February 2007 [37]. The AT-HIS is a standardized survey which is conducted at regular intervals in Austria (currently every eight years). The subjects included in the survey form a representative sample of the Austrian population. They were chosen from the central population register and are distributed across the different geographic regions of Austria. The AT-HIS is part of the European Health Interview Survey (E-HIS; http://www.euhsid.org), an important high-quality survey. The interviews were conducted by free-lancers engaged by the Austrian Statistic Agency. To ensure that all interviews were conducted in the same way, interviewers had to participate in a training day where they were instructed on how to conduct the survey. Time measurement, non-response analyses, and analyses of error dialogs were performed in order to ensure consistency between interview- ers. Additionally, all interviewers were supervised by field supervisors. Overall, 15474 individuals, aged 15 years and older, were questioned in computer-assisted personal interviews (CAPI; 54.7% female; response rate: 63.1%).

While 0.2% of the interviewees were pure vegetarians (57.7% female), 0.8% reported to be vegetarians consuming milk and eggs (77.3% female), and 1.2% to be vegetarians consuming fish and/ or eggs and milk (76.7% female). 23.6% reported to combine a carnivorous diet with lots of fruits and vegetables (67.2% female), 48.5% to eat a carnivorous diet less rich in meat (60.8% female), and 25.7% a carnivorous diet rich in meat (30.1% female). Since the three vegetarian diet groups included a rather small number of persons (N = 343), they were analyzed as one dietary habit group. Moreover, since the vegetarian group was the smallest, we decided to match each of the vegetarians (1) with an individual of each other dietary habit group (carnivorous diet rich in fruits and vegetables (2), carnivorous diet less rich in meat (3) and a carnivorous rich in meat (4)).

Matching Process

In a first step, subjects consuming a vegetarian diet were identified (N = 343). All vegetarians were categorized according to their sex, age (in age-groups spanning 5 years, e.g. 20- to 24-year- olds), and socioeconomic status (SES). Each such vegetarian was then matched with one subject consuming a carnivorous diet rich in fruits and vegetables, one individual eating a carnivorous diet less rich in meat, and one subject consuming a carnivorous diet rich in meat. Only 96.2% of the vegetarians were included in the analyses, since not all of them corresponded to a subject of the same sex, age, and SES from a different dietary habit group. Therefore, the total number of analyzed subjects was 1320 (comprising 330 vegetarians, 330 subjects consuming a carnivo- rous diet rich in fruits and vegetables, 330 individuals eating a carnivorous diet less rich in meat, and 330 subjects consuming a carnivorous diet rich in meat). Each dietary habit group was set-up according to the demographic characteristics shown in Table 1.

Ethical Approval

The study was carried out in compliance with the principles laid down in the Helsinki Declaration. No minors or children were included in the study. Verbal informed consent was obtained from all subjects, witnessed, and formally recorded. The Ethics Committee of the Medical University of Graz approved the consent procedure as well as the conductance of this study (EK- number: 24–288 ex11/12).

The Association between Nutrition and Health

Table 1. Data definition and structure for each of the four dietary habit groups.

Age Sex TOTAL
men women
SES N N N %
15–19 Low 3 22 25 7.6%
Middle 9 19 28 8.5%
High 0 1 1 0.3%
20–29 Low 4 11 15 4.5%
Middle 10 35 45 13.6%
High 5 13 18 5.4%
30–39 Low 3 10 13 3.9%
Middle 6 23 29 8.8%
High 6 11 17 5.2%
40–49 Low 4 6 10 3.0%
Middle 4 20 24 7.3%
High 8 16 24 7.3%
50–59 Low 3 7 10 3.0%
Middle 3 11 14 4.2%
High 1 6 7 2.1%
60–69 Low 3 7 10 3.0%
Middle 1 14 15 4.5%
High 0 2 2 0.6%
70–79 Low 4 8 12 3.6%
Middle 1 2 3 0.9%
High 0 0 0 0.0%
80+ Low 0 5 5 1.5%
Middle 0 3 3 0.9%
High 0 0 0 0.0%
TOTAL Low 24 76 100 30.3%
Middle 34 127 161 48.8%
High 20 49 69 20.9%
TOTAL 78 252 330 100.0%

Note. Data source: Austrian Health Interview Survey (AT-HIS) 2006/07.

N = number of subjects. Analyses were calculated with subjects matched according to their age, sex, and socio-economic status. Each dietary habit group consisted of 330 subjects with the above shown demographic characteristics (330 vegetarians, 330 subjects consuming a carnivorous diet rich in fruits and vegetables, 330 individuals eating a carnivorous diet less rich in meat, and 330 subjects consuming a carnivorous diet rich in meat; N = 1320). SES: A low SES corresponds a SES score between $3 and #6, a middle SES between .6 and # 10, and a high SES a score between .10 and #15. doi:10.1371/journal.pone.0088278.t001

Variables and Measurements

Face-to-face interviews were conducted by questioning the subjects about their socio-demographic characteristics, health- related behavior, diseases, medical treatments, and also psycho- logical aspects.

The independent variable in this study was the dietary habit of individuals. Concerning eating behavior, the respondents were given a list of six different dietary habits and asked which one describes their eating behavior best (1 = vegan, 2 = vegetarian eating milk/eggs, 3 = vegetarian eating fish and/or milk/eggs, 4 = carnivorous diet rich in fruits and vegetables, 5 = carnivorous diet less rich in meat, 6 = carnivorous diet rich in meat).

PLOS ONE | www.plosone.org 2 February 2014 | Volume 9 | Issue 2 | e88278

Participants described their dietary habit, without interviewers giving a clear definition of the various eating categories. Since, overall, only 2.2% of all participants consumed a vegetarian diet, these individuals were analyzed as one dietary habit group. We created a scale that would reflect the animal fat intake for each dietary habit (1 = vegetarian diet, 2 = carnivorous diet rich in fruits and vegetables, 3 = carnivorous diet less rich in meat, 4 = carniv- orous diet rich in meat).

Since age, sex, and the socioeconomic background of subjects all have an influence on health [38–41], we matched the subjects according to these variables in order to control for their influence. The SES of the subjects (ranging between 3 and 15) was calculated using the following variables: net equivalent income, level of education, and occupation. Net equivalent income was calculated based on an equivalence scale provided by the OECD [42], and divided by quintiles. Level of education was measured by an ordinal variable, distinguishing between (1) basic education (up to 15 years of age), (2) apprenticeship/vocational school, (3) secondary education without diploma, (4) secondary education with diploma, and (5) university education. The occupation of the subjects was differentiated into the following five levels: (1) unskilled worker, (2) apprentice/skilled worker, (3) self-em- ployed/middle job, (4) qualified job/academic, (5) executive position. To verify the combination of variables that served to calculate the SES, correlations with the different variables were calculated. They ranged between r = .70 and r = .80.

The body mass index (BMI) and lifestyle factors (physical activity, smoking, and alcohol consumption) were included as covariates in all analyses. The BMI was calculated by dividing the weight of a person in kilograms by the square of their height in meters (kg/m2) [43]. Physical exercise was measured using the short version of the International Physical Activity Questionnaire (IPAQ), a self-reported instrument, which asks for an estimate of the total weekly physical activity (walking, moderate- and vigorous-intensity activity) performed during the last week. The short version of the IPAQ does not discriminate between leisure- time and non-leisure time physical activity. The total MET score was calculated by weighting the reported minutes per week within each activity by a MET energy expenditure estimate that was assigned to each category [44]. Smoking behavior was measured as the number of cigarettes smoked per day. Alcohol consumption was surveyed as the number of days on which alcohol was consumed during the last 28 days.

The dependent variables focusing on ill-health included self- perceived health, ranging from 1 (very good) to 5 (very bad), and impairment to health, ranging from 1 (very impaired) to 3 (not impaired). We further assessed the presence of 18 specific chronic conditions (asthma, allergies, diabetes, cataract, tinnitus, hyper- tension, cardiac infarction, apoplectic stroke, bronchitis, arthritis, sacrospinal complaints, osteoporosis, urinary incontinence, gastric or intestinal ulcer, cancer, migraine, mental illness (anxiety disorder or depression), and any other chronic condition). Each condition was coded as present (1) or absent (0). We calculated a total frequency score by summing up the chronic conditions present (0–18, sum index). Additionally, a vascular risk score was calculated by summing up the variables ‘‘hypertension’’, ‘‘en- hanced blood cholesterol level’’, ‘‘diabetes’’, and ‘‘smoking’’ (0–4, sum index). Each variable was coded as present (1) or absent (0).

A dependent variable concerning health care was created as the sum index of the number of doctors consulted in the last 12 months (0–8, sum index). Each of the 8 medical treatments (general practitioner, gynecologist, urologist, dermatologist, oph- thalmologist, internist, orthopedist, and ENT physician) was coded as ‘‘consulted’’ (1) or ‘‘not consulted’’ (0). The number of

The Association between Nutrition and Health

andsex,age,socio-economic 28lastthedays) (N = 1320).
meatin p-value .000 .000 .002 .000 .150 .000 .003 .005 .033
3 4 4 4 4 3 4 4 4
carnivorous diet rich SD 0.87 0.61 1.60 0.73 1.22 2.13 1.05 withsubjects matched according to their which alcohol was consumed during
N= 330 M 1.57 2.73 1.03 1.98 1.60 3.61 1.26
habitdietarydifferentthebetweengroups. carnivorousdiet rich in fruits carnivorous diet less vegetablesand330=NvegetarianN = 330 rich in meat N = 330 MSDM SD M SD 1.500.941.78 0.90 1.46 0.87 2.710.662.62 0.62 2.72 0.59 1.001.601.29 1.64 0.92 1.29 1.960.742.02 0.75 2.01 0.71 1.681.331.69 1.27 1.43 1.02 3.652.283.22 2.15 3.59 2.02 1.391.071.25 1.07 1.29 1.07 Ndeviation,standard=SDmean,=M2006/07.= number of subjects, p = probability.
results,better day),percigarettesof(numberbehaviorsmokingand alcohol consumption (number of days on
calculatedcomparison.univariateresultAnalyseswereof
4
multivariate test result,
3
carehealthandhealthinDifferences2.Table Measure Health generallyhealthreported-Self Impairment conditionsChronic riskVascular careHealth doctor)thetovisitsof(numbertreatmentsMedical vaccinationsofNumber healthpreventiveofNumber usedofferscare HIS)-(ATSurveyInterviewHealthAustriansource:DataNote. 1 score),MET(totalactivityphysicalBMI,forcontrollingstatus doi:10.1371/journal.pone.0088278.t002
1 means
a higher score
2
1 results,
2 worse
1 2 means
2 1 score
a higher
PLOS ONE | www.plosone.org 3 February 2014 | Volume 9 | Issue 2 | e88278

The Association between Nutrition and Health

Table 3. Differences in suffering from various chronic conditions between the different dietary habit groups.

Carnivorous diet rich in Carnivorous diet less Carnivorous diet
Chronic condition Vegetarian fruits and vegetables rich in meat rich in meat p-value (x2)
Asthma 4.8% 3.3% 3.9% 4.5% .772
Allergies 30.6% 18.2% 20.3% 16.7% .000
Diabetes 2.7% 4.2% 2.4% 2.4% .455
Cataract 4.2% 3.0% 3.3% 1.8% .348
Tinnitus 4.8% 4.8% 4.8% 3.6% .840
Hypertension 11.5% 10.6% 12.4% 15.5% .260
Cardiac infarction 1.5% 1.5% 0.9% 0.6% .610
Apoplectic stroke 1.2% 1.8% 1.5% 1.8% .610
Bronchitis 3.9% 3.6% 2.4% 3.0% .701
Arthritis 8.5% 7.6% 8.8% 10.3% .662
Sacrospinal complaints 26.7% 24.8% 18.2% 23.9% .060
Osteoporosis 6.4% 4.8% 3.6% 5.8% .415
Urinary incontinence 2.1% 3.9% 2.7% 6.4% .023
Gastric or intestinal ulcer 4.2% 4.2% 1.5% 3.6% .169
Cancer 4.8% 3.3% 1.2% 1.8% .022
Migraine 15.8% 11.8% 9.1% 12.1% .074
Mental illness (anxiety 9.4% 4.8% 5.8% 4.5% .036
disorder or depression)
Any other chronic conditions 8.8% 5.5% 5.8% 6.7% .308

Note. Data source: Austrian Health Interview Survey (AT-HIS) 2006/07. Percentage of subjects suffering from the different chronic conditions. p (x2): probability value of Chi-Square-Test. Analyses were calculated with subjects matched according to their age, sex, and socio-economic status (N = 1320). doi:10.1371/journal.pone.0088278.t003

vaccinations was analyzed by calculating a sum index combining 8 different vaccinations (influenza, tetanus, diphtheria, polio, FSME, pneumococci, hepatitis A and B; 0–8, sum index). Each vaccination was coded as present (1) or absent (0). In addition, preventive health care was analyzed by calculating a sum index of the variables ‘‘preventive check-ups’’, ‘‘mammography’’, ‘‘prostate gland check-up’’, and ‘‘Papanicolaou test’’ (0–4, sum index). Each variable was coded as present (1) or absent (0).

The dependent variable concerning quality of life was measured using the short version of the WHOQOL (WHOQOL-BREF) [45]. Four domain scores (physical health, psychological health, social relationships, and environment) were calculated. These domain scores ranged between 4 and 20.

Statistical Analysis

In a first step subjects with different dietary habits (vegetarian, carnivorous diet rich in fruits and vegetables, carnivorous diet less rich in meat, carnivorous diet rich in meat) were matched according to their sex, age, and SES. Differences in lifestyle factors (BMI, total MET score, number of cigarettes smoked per day, and alcohol consumption in the last four weeks) between the different dietary habit groups were calculated by multivariate analysis of variance.

In order to analyze the differences between the dietary habit groups, multivariate analyses of variance were calculated for the three domains: (1) health (self-reported health, impairment due to health problems, number of chronic conditions, vascular risk), (2) health care (number of visits to the doctor, number of vaccinations, number of used preventive care offers), and (3) quality of life (physical and psychological health, social relation- ships, and environment). To address the bias of lifestyle factors impacting health, analyses of variance were calculated, controlling

for the aforementioned lifestyle variables (BMI, physical activity, smoking behavior, and alcohol consumption).

In the domain of ‘‘health’’, the two variables ‘‘self-reported health’’ and ‘‘impairment due to health problems’’ were originally assessed using an ordinal scale. Therefore, we controlled the results using non-parametric tests (Kruskal Wallis Test). Since the results were the same, only results of the analyses of variance are reported.

In addition, Chi-square tests were calculated for the aforemen- tioned 18 chronic conditions in order to establish which one occurs significantly more often, depending on the form of nutrition. p- values ,.050 were considered as statistically significant. All analyses were calculated using IBM SPSS software (version 20.0) for Windows.

Results

Participant Characteristics and Lifestyle Differences between the Dietary Habit Groups

In total, we analyzed the data of 1320 individuals (330 in each dietary habit group). Each dietary habit group was set-up according to the demographic characteristics shown in Table 1. Overall, 23.6% of all subjects were male and 76.4% female. 40.0% of the individuals were younger than 30 years, 17.8% between 30 and 39 years, 17.6% between 40 and 49 years, 9.4% between 50 and 59 years, 8.4% between 60 and 69 years, 4.4% between 70 and 79 years, and 2.4% than 80 years or older. 30.3% of the subjects had a low SES (they had an SES score of #6), 48.8% a middle one (SES between .6 and #10), and 20.9% had a high SES (SES.10).

Our multivariate analysis regarding lifestyle showed a significant main effect for the dietary habit of individuals (p = .000), showing

PLOS ONE | www.plosone.org 4 February 2014 | Volume 9 | Issue 2 | e88278

that the different dietary habit groups differ in their overall health behavior. However, results of the univariate analyses showed that the dietary habit groups only differ concerning their BMI and their alcohol consumption.

Concerning BMI: vegetarians have the lowest mean BMI (M = 22.9), followed by subjects eating a carnivorous diet less rich in meat (M = 23.4), rich in fruits and vegetables (M = 23.5), and rich in meat (M = 24.9). Heavy meat eaters differ significantly from all other groups in terms of their BMI (p = .000).

Concerning physical exercise: no significant difference was found in the total MET score between the various dietary habit groups (p = .631).

Concerning smoking behavior: the number of cigarettes smoked per day did not differ between the various dietary habit groups (p = .302).

Concerning alcohol consumption: Subjects following a vegetar- ian diet (M = 2.6 days in the last 28 days) or a carnivorous diet rich in fruits and vegetables (M = 3.0 days) consume alcohol signifi- cantly less frequently than those eating a carnivorous diet less rich in meat (M = 4.4 days) or rich in meat (M = 4.8 days; p = .000).

Health Differences between the Dietary Habit Groups

In the domain of health, the multivariate analysis of variance showed a significant main effect for the dietary habit of individuals (p = .000). Overall, vegetarians are in a poorer state of health compared to the other dietary habit groups. Concerning self- reported health, vegetarians differ significantly from each of the other groups, toward poorer health (p = 000). Moreover, these subjects report higher levels of impairment from disorders (p = .002). Vegetarians additionally report more chronic diseases than those eating a carnivorous diet less rich in meat (p = .000; Table 2). Significantly more vegetarians suffer from allergies, cancer, and mental health ailments (anxiety, or depression) than the other dietary habit groups (Table 3). Subjects who eat a carnivorous diet rich in meat more often report urinary incontinence (p = .023). No differences between individuals consuming different forms of diet were found regarding their vascular risk (p = .150; Table 2).

Differences in Health Care between the Dietary Habit Groups

Our multivariate analysis regarding health care has shown a significant main effect for dietary habits (p = .000) and confirmed that, overall, subjects with a lower animal fat intake demonstrate worse health care practices. Vegetarians and subjects eating a carnivorous diet rich in fruits and vegetables consult doctors more often than those eating a carnivorous diet less rich in meat (p = .003). Moreover, vegetarians are vaccinated less often than all other dietary habit groups (p = .005) and make use of preventive check-ups less frequently than subjects eating a carnivorous diet rich in fruits and vegetables (p = .033; Table 2).

Differences in Quality of Life between the Dietary Habit Groups

Regarding quality of life, the main effect of the multivariate analysis of variance showed no significant difference between the dietary habit groups (p = .291). The results obtained in the univariate analyses of variance, however, revealed that vegetarians have a lower quality of life in the domains of ‘‘physical health’’ (p = .026) and ‘‘environment’’ (p = .037) than subjects consuming a carnivorous diet less rich in meat. Moreover, vegetarians have a lower quality of life regarding ‘‘social relationships’’ than individuals eating a carnivorous diet rich in fruits and vegetables,

The Association between Nutrition and Health

value-p .291 .026 .116 .043 .037 BMI,forphysical
2 3 3 3 3
carnivorous diet rich in meat SD 2.86 2.24 16.88 2.63 16.45 2.08 sex, and socio-economic status controlling
N= 330 M 17.40 16.66 last 28 days) (N = 1320).
carnivorous diet less rich in M SD 2.90 2.33 16.96 2.38 16.56 1.98 subjects matched according to their age, alcohol was consumed during the
meat N = 330 17.68 16.88 p = probability.
dietarydifferentthebetweenlife habit groups. carnivorous diet rich in fruits 330=Nvegetarianand vegetables N = 330 SDM M SD 3.2617.16 17.52 2.95 2.7416.50 16.75 2.42 2.8216.59 16.99 2.49 2.2616.16 16.44 2.11
mean.=M2006/07.HIS)-(ATSurveySD = standard deviation. N = numbersubjects.of result,testmultivariate andday),percigarettesof(numberalcohol consumption (number of dayswhichon
result ofcomparison.univariatecalculatedAnalyseswerewith
3
qualityinDifferences4.Tableof Measure lifeofQuality healthphysicalWHOQOL healthpsychologicalWHOQOL relationshipssocialWHOQOL environmentWHOQOL InterviewHealthAustriansource:DataNote. 1 behaviorsmokingscore),MET(totalactivity doi:10.1371/journal.pone.0088278.t004
2
1 1 results,
1 1 better
a higher score means
PLOS ONE | www.plosone.org 5 February 2014 | Volume 9 | Issue 2 | e88278

or those with a carnivorous diet less rich in meat (p = .043). All results are shown in Table 4.

Discussion

Overall, our findings reveal that vegetarians report poorer health, follow medical treatment more frequently, have worse preventive health care practices, and have a lower quality of life. Concerning the variable ‘‘eating behavior’’, we tried to generate a variable that would reflect the animal fat intake (1 = vegetarian, 2 = carnivorous diet rich in fruits and vegetables, 3 = carnivorous diet less rich in meat, 4 = carnivorous diet rich in meat). The mean BMI of subjects is coupled in nearly linear progression with the amount of animal fat intake. This is in line with previous studies showing vegetarians to have a lower body mass index [1,4,5,7,9– 12].

Our results have shown that vegetarians report chronic conditions and poorer subjective health more frequently. This might indicate that the vegetarians in our study consume this form of diet as a consequence of their disorders, since a vegetarian diet is often recommended as a method to manage weight [10] and health [46]. Unfortunately, food intake was not measured in more detail, e.g. caloric intake was not covered. Hence, further studies will be necessary to analyze health and its relationship with different forms of dietary habits in more detail.

When analyzing the frequency of chronic diseases, we found significantly higher cancer incidence rates in vegetarians than in subjects with other dietary habits. This is in line with previous findings, reporting that evidence about cancer rates, abdominal complaints, and all-cause mortality in vegetarians is rather inconsistent [5–7,19–22]. The higher cancer incidence in vege- tarians in our study might be a coincidence, and is possibly related to factors other than the general amount of animal fat intake, such as health-conscious behavior, since no differences were found regarding smoking behavior and physical activity in Austrian adults as reported in other studies for other countries [9,13,14]. Therefore, further studies will be required in Austria in order to analyze the incidence of different types of cancer and their association with nutritional factors in more depth.

Several studies have shown the mental health effects of a vegetarian diet to be divergent [9,15,16]. Vegetarians in our study suffer significantly more often from anxiety disorder and/or depression. Additionally, they have a poorer quality of life in terms of physical health, social relationships, and environmental factors.

Moreover, the use of health care differs significantly between the dietary habit groups in our study. Vegetarians need more medical treatment than subjects following another form of diet. However, this might be due to the number of chronic conditions, which is higher in subjects with a vegetarian diet.

Among the strengths of our study are: the large sample size, the matching according to age, sex, and socioeconomic background, and

References

1.American Dietetic Association, Dietitians of Canada (2003) Position of the American Dietetic Association and Dietitians of Canada: vegetarian diets. Can J Diet Pract Res 64(2): 62–81.

2.Craig WJ (2009) Health effects of vegan diets. Am J Clin Nutr 89(5): 1627s– 1633s.

3.Craig WJ (2010) Nutrition concerns and health effects of vegetarian diets. Nutr Clin Pract 25(6): 613–20.

4.Craig WJ, Mangels AR, American Dietetic Association (2009) Position of the American Dietetic Association: vegetarian diets. J Am Diet Assoc 109(7): 1266– 82.

5.Dwyer JT (1988) Health aspects of vegetarian diets. Am J Clin Nutr 48: 712–38.

6.Key TJ, Appleby PN, Davey GK, Allen NE, Spencer EA, et al. (2003) Mortality in British vegetarians: review and preliminary results from EPIC-Oxford. Am J Clin Nutr 78: 533s–58s.

The Association between Nutrition and Health

the standardized measurement of all variables. Other strengths of our study include considering the influence of weight and lifestyle factors on health, e.g. physical exercise and smoking behavior.

Potential limitations of our results are due to the fact that the survey was based on cross-sectional data. Therefore, no statements can be made whether the poorer health in vegetarians in our study is caused by their dietary habit or if they consume this form of diet due to their poorer health status. We cannot state whether a causal relationship exists, but describe ascertained associations. More- over, we cannot give any information regarding the long-term consequences of consuming a special diet nor concerning mortality rates. Thus, further longitudinal studies will be required to substantiate our results. Further limitations include the measure- ment of dietary habits as a self-reported variable and the fact that subjects were asked how they would describe their eating behavior, without giving them a clear definition of the various dietary habit groups. However, a significant association between the dietary habit of individuals and their weight and drinking behavior is indicative for the validity of the variable. Another limitation concerns the lack of detailed information regarding nutritional components (e.g. the amount of carbohydrates, cholesterol, or fatty acids consumed). Therefore, more in-depth studies about nutri- tional habits and their effects on health are required among Austrian adults. Further studies should e.g. investigate the influence of the various dietary habits on the incidence of different cancer types. To our knowledge this is the first study ever in Austria to analyze differences in terms of dietary habits and their impact on health. We admit that the large number of participants made it necessary to keep the questions simple, in order to cover the large sample. Overall, we feel that our results are of specific interest and contribute to extant scientific knowledge, notwith- standing some limitations regarding causes and effects.

Conclusions

Our study has shown that Austrian adults who consume a vegetarian diet are less healthy (in terms of cancer, allergies, and mental health disorders), have a lower quality of life, and also require more medical treatment. Therefore, a continued strong public health program for Austria is required in order to reduce the health risk due to nutritional factors. Moreover, our results emphasize the necessity of further studies in Austria, for a more in- depth analysis of the health effects of different dietary habits.

Author Contributions

Conceived and designed the experiments: NTB WF. Performed the experiments: NTB. Analyzed the data: NTB JM FG ER WF. Contributed reagents/materials/analysis tools: NTB JM FG WF. Wrote the paper: NTB ER WF.

7.Key TJ, Appleby PN, Rosell MS (2006) Health effects of vegetarian and vegan diets. Proc Nutr Soc 65(1): 35–41.

8.Deriemaeker P, Alewaeters K, Hebbelinck M, Lefvre J, Philippaerts R, et al. (2010) Nutritional status of Flemish vegetarians compared with non-vegetarians: a matched sample study. Nutrients 2(7): 770–80.

9.Baines S, Powers J, Brown WJ (2007) How does the health and well-being of young Australian vegetarian women compare with non-vegetarians? Public Health Nutr 10(5): 436–42.

10.Farmer B, Larson BT, Fulgoni VL, Rainville AJ, Liepa GU (2011) A vegetarian dietary pattern as a nutrient-dense approach to weight management: an analysis of the national health and nutrition examination survey 1999–2004. J Am Diet Assoc 111(6): 819–27.

PLOS ONE | www.plosone.org 6 February 2014 | Volume 9 | Issue 2 | e88278

11.Rizzo NS, Sabate´ J, Jaceldo-Siegl K, Fraser GE (2011) Vegetarian dietary patterns are associated with a lower risk of metabolic syndrome: the adventist health study 2. Diabetes Care 34(5): 1225–27.

12.Tonstad S, Butler T, Yan R, Fraser GE (2009) Type of vegetarian diet, body weight, and prevalence of type 2 diabetes. Diabetes care 32(5): 791–96.

13.Pollard J, Greenwood D, Kirk S, Cade J (2001) Lifestyle factors affecting fruit and vegetable consumption in the UK women’s cohort study. Appetite 37(1): 71–79.

14.Gacek M (2010) Selected lifestyle and health condition indices of adults with varied models of eating. Rocz Pantsw Zakl Hig 61(1): 65–69.

15.Low Dog T (2010) The role of nutrition in mental health. Altern Ther Health Med 16(2): 42–46.

16.Michalak J, Zhang XC, Jacobi F (2012) Vegetarian diet and mental disorders: results from a representative community survey. Int J Behav Nutr Phys Act 9: 67.

17.Singh PN, Sabate´ J, Fraser GE (2003) Does low meat intake increase life expectancy in humans? Am J Clin Nutr 78(3): 526s–32s.

18.McEvoy CT, Temple N, Woodside JV (2012) Vegetarian diets, low-meat diets and health: a review. Public Health Nutr 15: 2287–2294.

19.Appelby PN, Thorogood M, Mann JI, Key TJA (1999) The Oxford vegetarian study: an overview. Am J Clin Nutr 70: 525s–31s.

20.Frentzel-Beyme R, Chang-Claude J (1994) Vegetarian diets and colon cancer: the German experience. Am J Clin Nutr 59: 143s–52s.

´

21. Burkert NT, Großscha¨dl F, Muckenhuber J, Ra´sky E, Stronegger WJ, et al. (2012) Gastro-intestinal complaints related to various eating behaviours. J Nutr Therapeutics 1: 19–23.

22. Tantamango-Bartley Y, Jaceldo-Siegl K, Fan J, Fraser G (2013) Vegetarian Diets and the Incidence of Cancer in a Low-risk Population. Cancer Epidemiol Biomarkers Prev 22(2). DOI: 10.1158/1055-9965.EPI-12.1060.

23. Flood A, Velie AM, Sinha R, Chaterjee N, Lacey JV, et al. (2003) Meat, fat, and their subtypes as risk factors for colorectal cancer in a prospective cohort study in women. Am J Epidemiol 158: 59–68.

24. Mathew A, Peters U, Chatterjee N, Kulldorff M, Sinha R (2004) Fat, fiber, fruits, vegetables, and risk of colorectal adenomas. Int J Cancer 108: 287–292.

25. Seow A, Quah SR, Nyam D, Straughan PT, Chua T, et al. (2002) Food groups and the risk of colorectan carcinomas in an Asian population. Cancer 95: 2390– 2396.

26. Vang A, Singh PN, Lee JW, Haddad EH, Brinegar CH (2008) Meats, processed meats, obesity, weight gain and occurrence of diabetes among adults: findings from Adventist Health Studies. Ann Nutr Metab 52(2): 96–104.

27. Boutron-Ruault MC, Senesse P, Meance S, Belghiti C, Faivre J (2001) Energy intake, body mass index, physical activity, and the colorectal adenoma- carcinoma sequence. Nutr Cancer 39: 50–57.

28. Appleby PN, Key TJ, Thorogood M, Burr ML, Mann J (2002) Mortality in British vegetarians. Public Health Nutr 5(1): 29–36.

29. Chang-Claude J, Hermann S, Eilber U, Steindorf K (2005) Lifestyle determinants and mortality in German vegetarians and health-conscious persons: results of a 21-yearfollow-up. Cancer Epidemiol Biomarkers Prev 14(4): 963–68.

30. Fraser GE (2009) Vegetarian diets: what do we know of their effects on common chronic diseases? Am J Clin Nutr 89: 1607s–12s.

The Association between Nutrition and Health

31.Sabate´ J (2003a) The contribution of vegetarian diets to health and disease: a paradigm shift? Am J Clin Nutr 78: 502s–7s.

32.Sabate´ J (2003b) The contribution of vegetarian diets to human health. Forum Nutr 56: 218–20.

33.Karlic H, Schuster D, Varga F, Klindert G, Lapin A, et al. (2008) Vegetarian diet affects genes of oxidative metabolism and collagen synthesis. Ann Nutr Metab 53(1): 29–32.

34.Kornsteiner M, Singer I, Elmadfa I (2008) Very low n-3long-chain polyunsaturated fatty acid status in Austrian vegetarians and vegans. Ann Nutr Metab 52(1): 37–47.

35.Majchrzak D, Singer I, Maenner M, Rust P, Genser D, et al. (2006) B-vitamin status and concentrations of homocysteine in Austrian omnivores, vegetarians and vegans. Ann Nutr Metab 50(6): 485–91.

36.Schumacher M, Eber B, Schallmoser K, Toplak H, Zweiker R, et al. (1993) Eating behavior of patients with metabolic diseases and metabolically healthy probands in Austria. Results of a questionnaire survey at the Graz Autumn Fair 1991. Wien Med Wochenschr 43(12): 329–23.

37.Klimont J, Kytir J, Leitner B (2007) Austrian Health Interview Survey 2006/07. (Oesterreichische Gesundheitsbefragung 2006/07. Hauptergebnisse und meth- odische Dokumentation.) Wien: Statistik Austria.

38.Bauer GF, Huber CA, Jenny GJ, Mueller F, Haemming O (2009) Socioeconomic status, working conditions and self-rated health in Switzerland: explaining the gradient in men and women. International J Pub Health 54: 23– 30.

39.Volkert, D (2006) The body mass index (BMI) – an important parameter to evaluate the nutritional status [Der Body-Mass-Index (BMI) – ein wichtiger Parameter zur Beurteilung des Erna¨hrungszustandes]. Aktuel Ernaehr Med 31: 126–132.

40.Dorner TE, Rieder A (2010) Obesity paradox or reverse epidemiology: is hight body weight a protective factor for various chronic conditions? [Das Adipositasparadoxon oder Reverse Epidemiologie. Hohes Ko¨rpergewicht als protektiver Faktor bei bestimmten chronischen Bedingungen?] Dtsch Med Wochenschr 135: 413–418.

41.Burkert NT, Ra´sky E, Freidl W (2012) Social inequalities regarding health and health behaviour in Austrian adults. Wien klin Wochenschr 7–8:256–261.

42.OECD Social Policy Division (2009) ‘‘What are equivalence scales?’’ Available: http://www.oecd.org/els/social.

43.World Health Organization (2013) Global database on Body Mass Index. BMI classification. Available: http://apps.who.int/bmi/index.jsp?introPage = intro_3.html. Accessed 2013 September 17.

44.Craig CL, Marshall A, Sjostrom M, Bauman AE, Booth ML et al. (2003) International Physical Activity Questionnaire: 12 country reliability and validity. Med Sci Sports Exerc 35(8): 1381–1395.

45.World Health Organization (1996) WHOQOL-BREF. Introduction, Adminis- tration, Scoring, and Generic Version of the Assessment. Geneva: WHO. Available: http://www.who.int/mental_health/media/en/76.pdf.

46.Leitzmann C (2005) Vegetarian diets: what are the advantages? Forum Nutr 57: 147–56.

bookmark_borderGlobal Warming Exponential Damage

The U.N. Intergovernmental Panel on Climate Change reported that global warming is spiraling out of control. “The world, in many cases, is ill-prepared for risks from a changing climate,” the IPCC said.

FAQ 1: Are risks of climate change mostly due to changes in extremes, changes in average climate, or both?

People and ecosystems across the world experience climate in many different ways, but weather and climate extremes strongly influence losses and disruptions. Average climate conditions are important. They provide a starting point for understanding what grows where and for informing decisions about tourist destinations, other business opportunities, and crops to plant. But the impacts of a change in average conditions often occur as a result of changes in the frequency, intensity, or duration of extreme weather and climate events. It is the extremes that place excessive and often unexpected demands on systems poorly equipped to deal with those extremes. For example, wet conditions lead to flooding when storm drains and other infrastructure for handling excess water are overwhelmed. Buildings fail when wind speeds exceed design standards. For many kinds of disruption, from crop failure caused by drought to sickness and death from heat waves, the main risks are in the extremes, with changes in average conditions representing a climate with altered timing, intensity, and types of extremes.

FAQ 2: How much can we say about what society will be like in the future, in order to plan for climate change impacts?

Overall characteristics of societies and economies, such as population size, economic activity, and land use, are highly dynamic. On the scale of just one or two decades, and sometimes in less time than that, technological revolutions, political movements, or singular events can shape the course of history in unpredictable ways. To understand potential impacts of climate change for societies and ecosystems, scientists use scenarios to explore implications of a range of possible futures. Scenarios are not predictions of what will happen, but they can be useful tools for researching a wide range of “what if” questions about what the world might be like in the future. They can be used to study future emissions of greenhouse gases and climate change. They can also be used to explore the ways climate-change impacts depend on changes in society, such as economic or population growth or
progress in controlling diseases. Scenarios of possible decisions and policies can be used to explore the solution space for reducing greenhouse gas emissions and preparing for a changing climate. Scenario analysis creates a foundation for understanding risks of climate change for people, ecosystems, and economies across a range of possible futures. It provides important tools for smart decision-making when both uncertainties and consequences are large.

FAQ 3: Why is climate change a particularly difficult challenge for managing risk?

Risk management is easier for nations, companies, and even individuals when the likelihood and consequences of possible events are readily understood. Risk management becomes much more challenging when the stakes are higher or when uncertainty is greater. As the WGII AR5 demonstrates, we know a great deal about the impacts of climate change that have already occurred, and we understand a great deal about expected impacts in the future. But many uncertainties remain, and will persist. In particular, future greenhouse gas emissions depend on societal choices, policies, and technology advancements not yet made, and climate-change impacts depend on both the amount of climate change that occurs and the effectiveness of development in reducing exposure and vulnerability. The real challenge of dealing effectively with climate change is recognizing the value of wise and timely decisions in a setting where complete knowledge is impossible. This is the essence of risk management.

bookmark_borderWashington Mudslide

You would think with all the mud slinging in Washington DC that would be the Washington with the mudslide. No, the mudslide that killed over a dozen people and left over 100 missing was in Oso, Washington. Oso is a small village 55 miles northeast of Seattle (or, perhaps we should say *was*.) The village was “obliterated” after weeks of heavy rain.

This sort of extreme weather event is expected to become more normal due to the effects of global warming.